
21. 9) B – Biosecurity & Epidemiology
B · Biosecurity & Epidemiology = “How fast do we detect and drive Rₜ<1 while sustaining clinical care and lab throughput?” (detection speed & containment capacity)
Biosecurity & Epidemiology is the discipline that keeps a cough from becoming a season. BSL-2/3 rooms you actually use; sterilized cargo lanes; sentinel coverage with cadence; on-hub reagents and vaccine platforms. What moves it is rehearsal under uncertainty and a reagent pantry that never goes empty by surprise. Proof is an outbreak exercise where the reproduction number drops below one by the second week and first doses roll before the month is out. Failure is quarantine theater and stockouts explained by adjectives.
Quick Heuristic: B vs S (Shock Isolation Resilience) can be confused. Best analogy: Fire brigade vs fireproof pantry. B is detect→respond to drive Rₜ<1. S is having PPE, cold-chain days, and routes to ride it out. Test: Was the gain time-to-control (B) or how long supplies last (S)?
Cross-pillar ties to B: S owns cold-chain days and no-arrivals continuity; G legitimizes emergency orders and publishes artifacts. P provides surge staffing; M and A localize steriles/reagents and diagnostic components. E guarantees power for labs and isolation; C raises compliance and lowers panic correlation.
Lessons Learnt: Move faster—after you delete the steps that never mattered. We pre-authorized protocols, trimmed signoffs, and built surveillance-first detection (wastewater/air/clinical) so that Rₜ < 1 became a clock we could hit. Labs won by TAT, not by room labels; isolation capacity mattered only if we could staff and power it.
Misjudged Initially:
Over-indexed on clinical testing; under-invested in wastewater/air sentinel networks.
Built AIIR rooms without surge staffing or ACH compliance.
Counted stockpile days instead of control-window availability (PPE, antivirals, vax).
Sequenced too little, too late; missed variant shifts.
Qs to Ask:
What is your median time to index isolation from first signal?
How many days of cold-chain for the current vaccine set, with a power failure?
What is your countermeasure coverage within control windows (PPE, antivirals, vax)?
Port Harmonia, Mars (Year 94 Mars Human Era)
Here is an example of Port Harmonia’s Biosecurity & Epidemiology MIS in the early third century HE:
B=0.20(0.78)+0.15(0.76)+0.15(0.85)+0.25(0.8)+0.15(0.75)+0.10(0.66)≈0.77
Calculations:
Bsurv: Coverage 0.85, TAT 0.8, Genomic 0.7 ⇒ 0.35⋅.85+0.30⋅.8+0.35⋅.7=0.78.
Blab: BSL-3 local (0.7), Menu 0.8, Throughput 0.7, QC/PT 0.9 ⇒ 0.30⋅.7+0.30⋅.8+0.25⋅.7+0.15⋅.9=0.76.
Bipc: 0.9, 0.85, 0.8 ⇒ 0.35⋅.9+0.35⋅.85+0.30⋅.8=0.85.
Bresp: surprise adverse drill with Rₜ<1 in 14 d ⇒ 0.8.
Biso: 0.75.
Bcmx: CM_coverage 0.7, Local_compounding 0.6 ⇒ 0.6⋅.7+0.4⋅.6=0.66.
Combine (weights sum to 1)
Simplified starting weights for B sub-scores (tuneable, disclosed). Why this split? Early detection + containment performance dominate; labs/IPC/isolation are enablers; countermeasure readiness closes the loop.
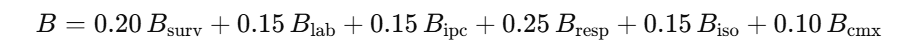
Interpretation:
B < 0.40 — Plans on paper; slow detection; limited isolation; drills unproven.
0.40 – 0.70 — Reliable detection; working labs; first live containment drills pass; isolation capacity adequate.
> 0.70 — Fast detect-to-respond; robust IPC; repeated surprise drills; real events contained quickly.